Every pediatric visit note answers to two readers: the next clinician who opens the chart and the payer reviewing the claim.
A note that's too vague for a colleague to act on is often also too vague to justify the service. And both readers see more recycled text than you'd expect: a 2022 study of more than 104 million notes at Penn Medicine found about half the text had been carried forward from earlier notes.
Here's how to check your EMR documentation against what payers audit, plus the template habits that keep every note specific.
What Is EMR Documentation?
EMR documentation is the clinical record a provider creates during and after a visit. It covers:
- History
- Physical exam
- Assessment
- Plan
- Orders
- Results
- Any related communication
Beyond billing and subsequent visits, the record is pulled for specialist referrals, school and camp forms, and families' records requests.
The Documentation Standards Payers Audit Against
Payers check notes against the general principles of E/M documentation from the Centers for Medicare and Medicaid Services (CMS), and many practices add their own compliance rules on top:
The former Northwestern Medical Faculty Foundation's policy went further on specificity, calling identical documentation across records a misrepresentation of the medical necessity requirement for coverage.
Best Practices for EMR Documentation
These seven habits distinguish documentation that holds up from documentation that doesn't:
- Chart in real time: CMS asks for documentation during the visit or as soon as possible afterward, since details fade fast and a note pieced together later is harder to defend. Watch for EMR habits that push documentation later, like creating a placeholder visit just to record a phone call, or waiting for a colleague to leave the chart before you can start charting.
- Name the historian: In pediatrics especially, the person who reports the symptom influences how it's weighed. The cough note below opens with "4-year-old seen with mother," which tells the next reader whose account the history rests on.
- Show the reasoning: A colleague can't weigh an assessment that they can't trace back to the findings.
- Make the plan actionable: State what happens next and what would change it. The cough note does this in one line: return if the cough lasts three weeks, fever comes back, or breathing gets harder.
- Record time when you bill by time: Office E/M visits can be coded on total time spent that day, so the note needs to include the minutes and what filled them. The time-billing section below walks through what counts and each code's minimum.
- Label late entries: Anything added after the visit should be marked as a late entry with the date it was written. According to the CMS Program Integrity Manual, the date and author of any delayed entry should be identifiable, and the addition should be clearly and permanently marked.
- Verify before you carry content forward: Anything copied from a prior note needs to be read and confirmed. The copy-paste section below shows what tends to go wrong when it isn't.
What Separates a Strong Note From a Weak One
A strong note is usually only a few sentences longer than a weak one, and those sentences include the details a colleague would otherwise have to ask about. Here's the same follow-up visit for a persistent cough, documented both ways. For four complete samples by visit type, see these pediatric SOAP note examples.
A weak note:
Patient seen for cough. Exam unremarkable. Continue current management. Follow up as needed.
Nothing is false, but this note doesn't mention who reported the cough or for how long, and nothing tells a colleague what should bring the child back.
A stronger version:
History: 4-year-old seen with mother. Mother reports a dry cough for 11 days, worse at night, no fever since day three. No wheeze, retractions, or decreased oral intake per mother's report.
Exam: Lungs clear bilaterally, no tachypnea, ears and throat clear.
Assessment: Post-viral cough favored over reactive airway disease given the absence of wheeze and the timeline.
Plan: Continue supportive care; no antibiotics indicated. Mother to return if the cough persists for three weeks, fever returns, or the work of breathing increases.
The second version adds three sentences. It names the historian, gives the reasoning behind the assessment, and sets return precautions a colleague could act on.
How to Build EMR Templates That Keep Every Note Specific
A good template asks what a visit type requires and leaves space for the answer, so every finding has to come from the exam you just did. Northwestern's compliance policy didn't permit pre-populated outcomes in templates at all. Most EMRs pre-fill normal findings anyway, so the safeguard is editing: before you sign, change or remove any default that doesn't match what you examined.
Also aim to:
- Keep templates short: A form that generates two pages of boilerplate buries the 20 words a colleague needs.
- Build them by visit type: A well child template and a sick visit template ask different questions.
- Review them annually: Templates drift out of date as guidance and payer rules change.
One way to audit your own templates is to read a finished note and mark any sentence that could have been written before the patient arrived. Those are the lines that an auditor will question first.
The Copy-Paste Problem
Copying a prior note forward saves time, and it's a common practice. A 2022 JAMA Network Open study of more than 104 million notes across the Penn Medicine health system found that 50.1% of the text had been duplicated from earlier notes about the same patient, up from 33% in 2015.
But as the Joint Commission warns, copying and pasting carries a risk of error propagation. Here's how that can play out:
Some institutions draw a hard line. Northwestern's policy barred copying the history of present illness, exam, assessment, and plan, and the Joint Commission recommends that organizations spell out what's permissible to copy.
If you copy anything, read it before signing and delete anything you wouldn't defend today.
What Pediatric Documentation Has to Capture
Pediatric notes carry extra weight, from family dynamics to dosing math. Here's what to include:
- The historian: In shared-custody or blended families, the note should name which caregiver gave the history and their relationship to the child.
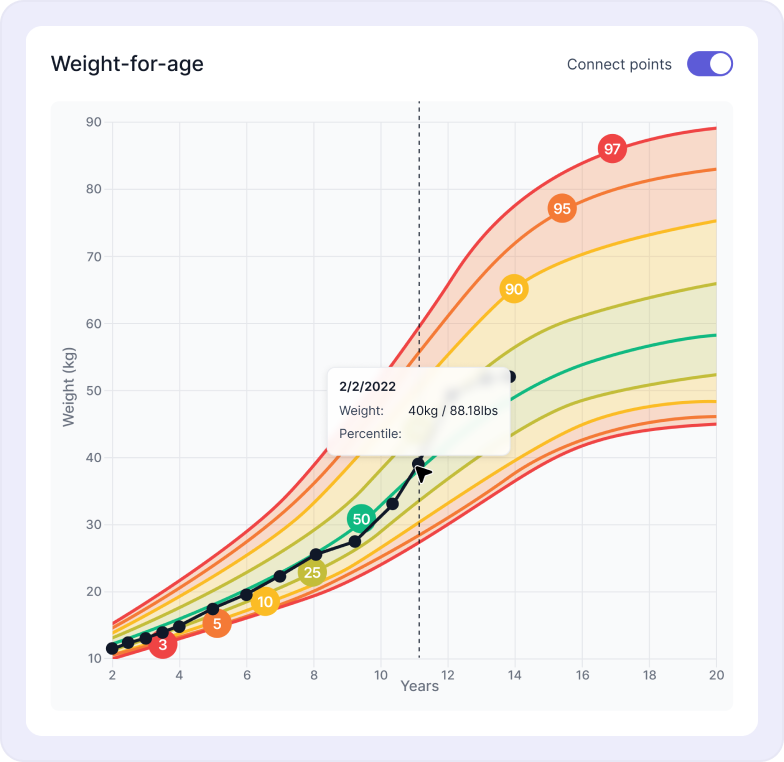
- Growth as a series: Measurements should be plotted against prior points, with the percentile stated. For a child born preterm, note that you're using corrected age, counted from the due date, through about age 2.
- Weight-based decisions: When dosing depends on current weight, the weight you use and the date it was measured should appear in the note.
- Anticipatory guidance: The AAP recommends age-specific anticipatory guidance at every well child visit, so the note should show what was covered.
- Vaccine counseling: Codes 90460 and 90461 (for patients through age 18) require face-to-face counseling by the physician or another qualified healthcare professional. The note needs to list each vaccine component and confirm that counseling covered all of them.
- Vaccine administration record: Federal law requires the vaccine's manufacturer and lot number, the date given, the name and title of the person who gave it, and the edition date of the Vaccine Information Statement (VIS) with the date it was provided. Record Vaccines for Children (VFC) eligibility as well, since it decides which inventory the dose came from.
- Refusals: When a family declines a vaccine, screening, or test, document what was offered, the reason given, and that the risks were discussed. The AAP Refusal to Vaccinate form is a common template for vaccines.
- Screening detail: For every developmental screening, and every behavioral or emotional screen, record the instrument, score, and interpretation together.
- Confidential content: When an adolescent consents to care on their own, mark that part of the note confidential so it stays hidden from the caregiver's family portal view. Then check the claim: a confidential service billed to a parent's plan can still reach the parent as an explanation of benefits.
Confidentiality is where EMRs built around adult care tend to fall short. Most records treat a note as a single object with a single audience, whereas pediatric practice requires parts of a note to be visible only to certain readers.
How to Document Time for Time-Based Billing
To bill an office visit by time, document the total minutes you spent on the patient on the date of the visit.
For office visit codes 99202–99205 and 99212–99215, you can pick the level by total time or by medical decision making (MDM), whichever the note supports better.
Time often works in your favor in pediatrics, where much of a visit is spent talking with a parent. An ADHD medication check, a new asthma action plan, or a behavior concern can run long on counseling while the MDM stays moderate.
What counts toward total time, according to the AMA's E/M guidelines:
- Before the visit: Reviewing test results, outside records, or a teacher's rating scales
- During the visit: Taking history from the child or caregiver, examining, and counseling the family
- After the visit: Placing orders, calling a specialist, and documenting in the EMR
What doesn't count:
- Clinical staff time: Rooming, vitals, and screenings that your medical assistant or nurse handles
- Separately billed services: Time spent on a service with its own code, like vaccine counseling billed with 90460
- Travel and general teaching: Driving between sites or teaching that isn't about this patient
You only need the total. The AMA doesn't require start and stop times or minutes per task, so one line at the end of the note covers it. Here's what that looks like for a 9-year-old's ADHD follow-up:
Total time on date of service: 42 minutes, including review of teacher rating scales, counseling the patient and father on medication options, and documentation.
At 42 minutes, that visit clears the 40-minute minimum for 99215, even if the MDM alone would support 99214. Each office visit level has its own minimum:
If a visit runs at least 15 minutes past the 99205 or 99215 minimum, add-on code 99417 covers the extra time. Medicare uses its own code, G2212, which starts later. Some payers follow Medicare's rules, so check each payer's policy before you bill.
Well child visits work differently. Preventive medicine codes aren't time-based, so the minutes you spend at a checkup don't change the code. If a problem at the checkup takes significant extra work, report it as its own office visit with modifier 25. A minor issue handled during the checkup stays part of the preventive code.
To make time capture part of your routine, add a total-time field to your sick visit and follow-up templates, but treat the number it collects with caution. Providers move between patients throughout the day, and total time includes reviewing records and results before and after the visit, not just time in the exam room, so a figure entered at signing is often an estimate. Note the minutes as you go, so the total you document is one you could defend.
Capture Every Pediatric Detail in Your EMR Documentation
Develo supports pediatric EMR documentation with an AI scribe that drafts each note from that visit's conversation and chart data, plus templates built for each pediatric visit type, so you're not relying on memory to capture the details listed above.
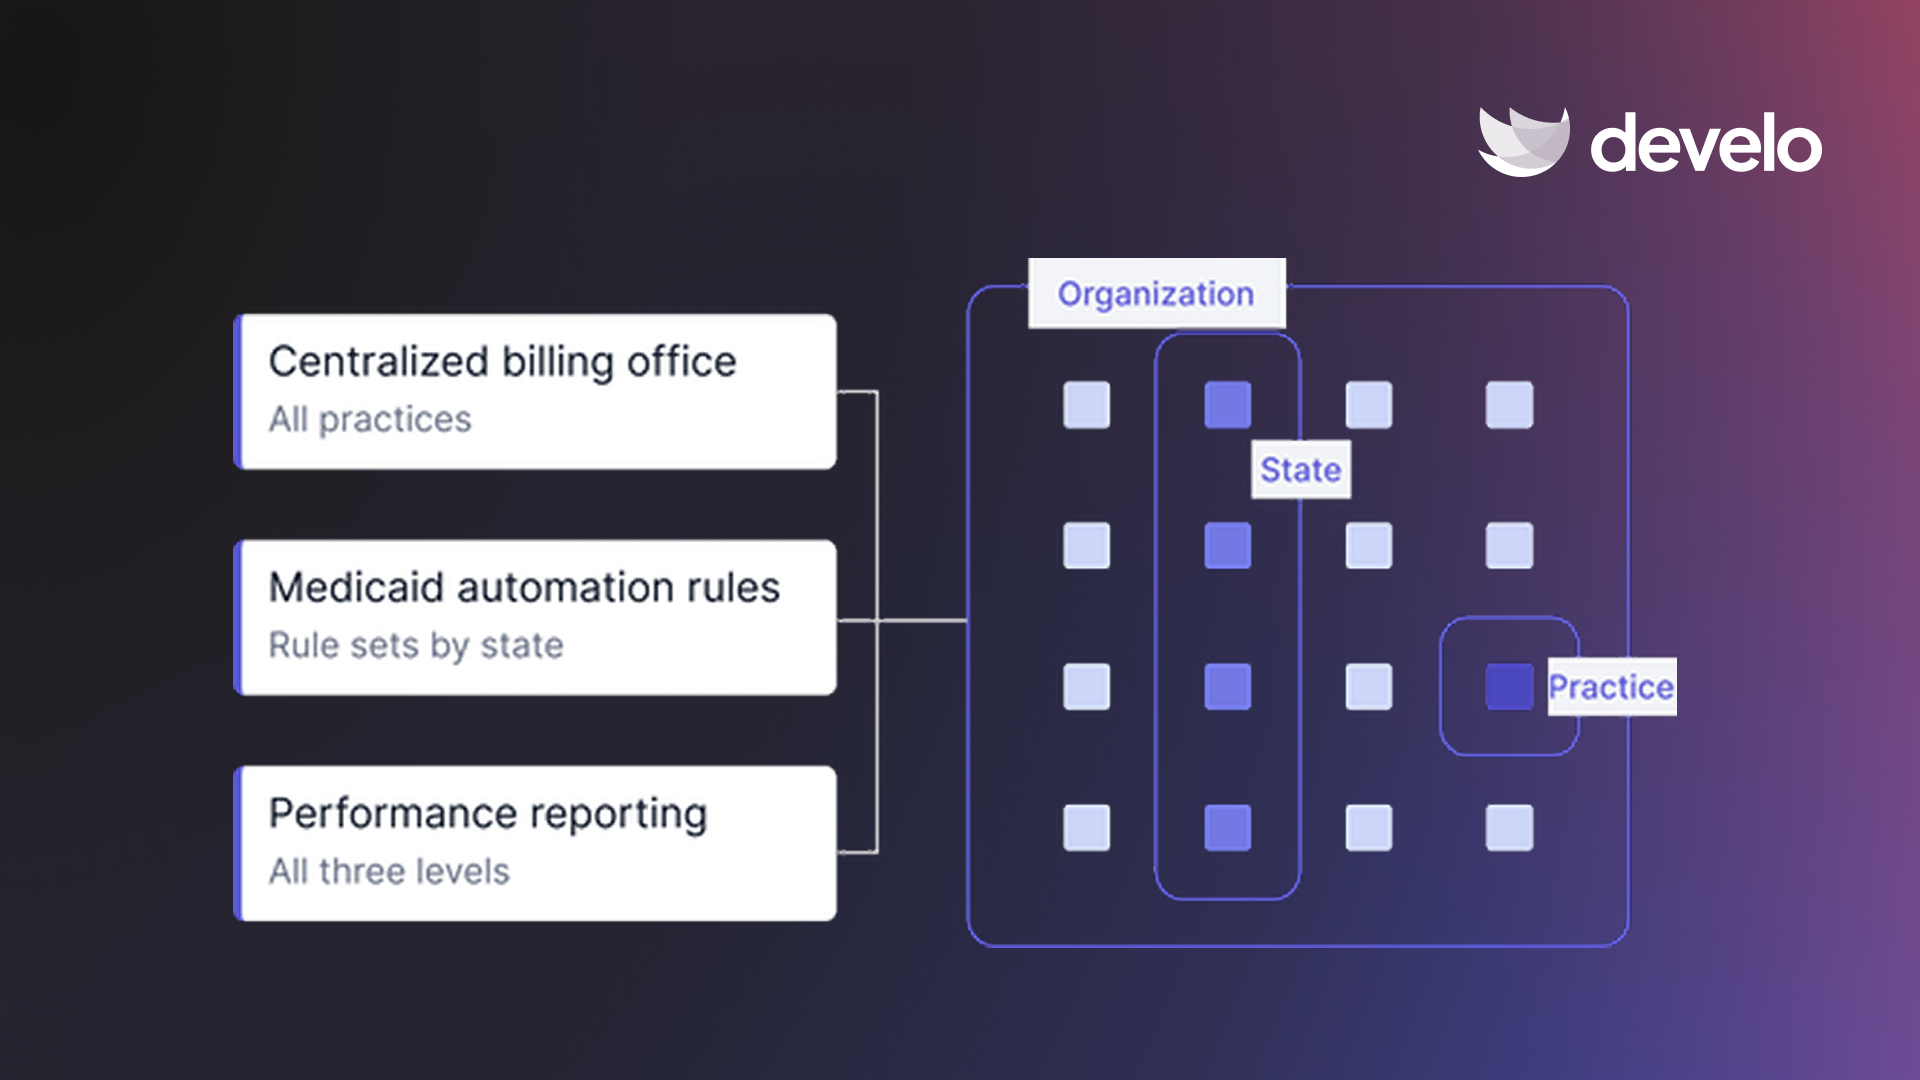
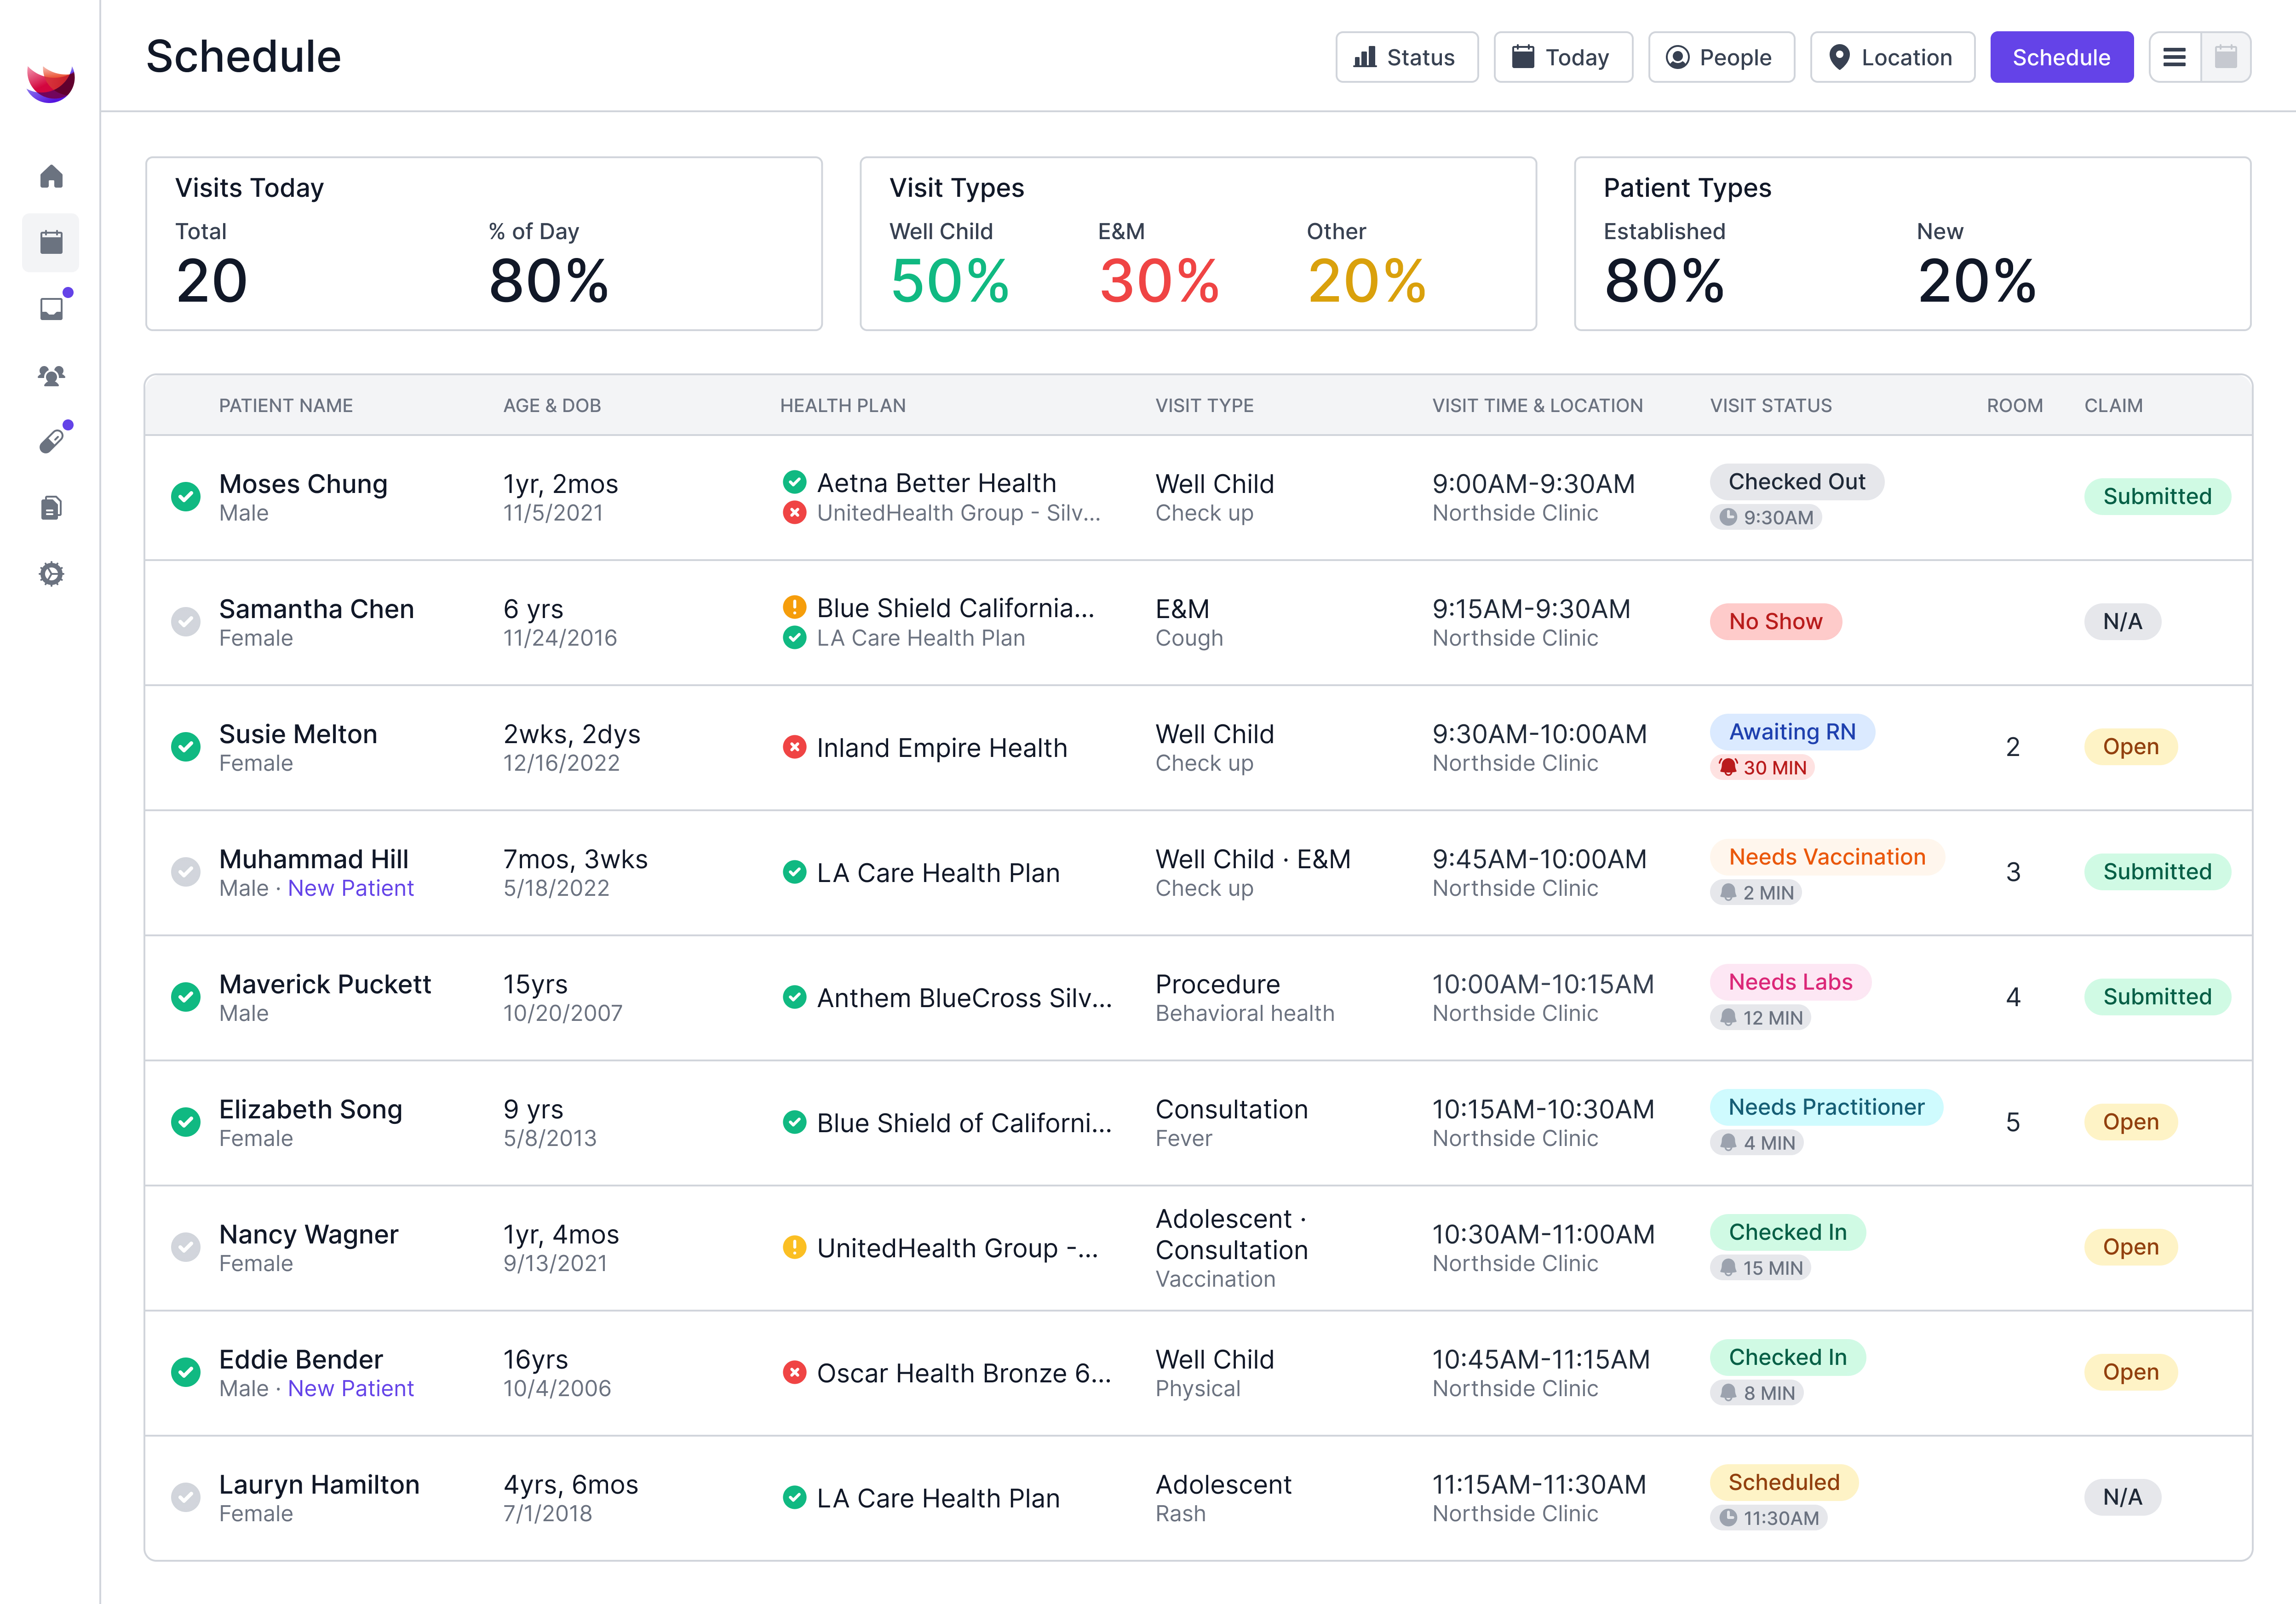
As the AI-native operating system for pediatrics, Develo unifies charting, billing, practice management, and family engagement in one system built solely for pediatric practices, so the note you sign feeds the claim directly, with no re-entry.
- Develo AI scribe: This tool draws on the conversation and pertinent chart data like growth, immunizations, and screening results to write into your visit note, and suggests diagnosis codes and the E/M level for you to review. You approve every section before it's added.
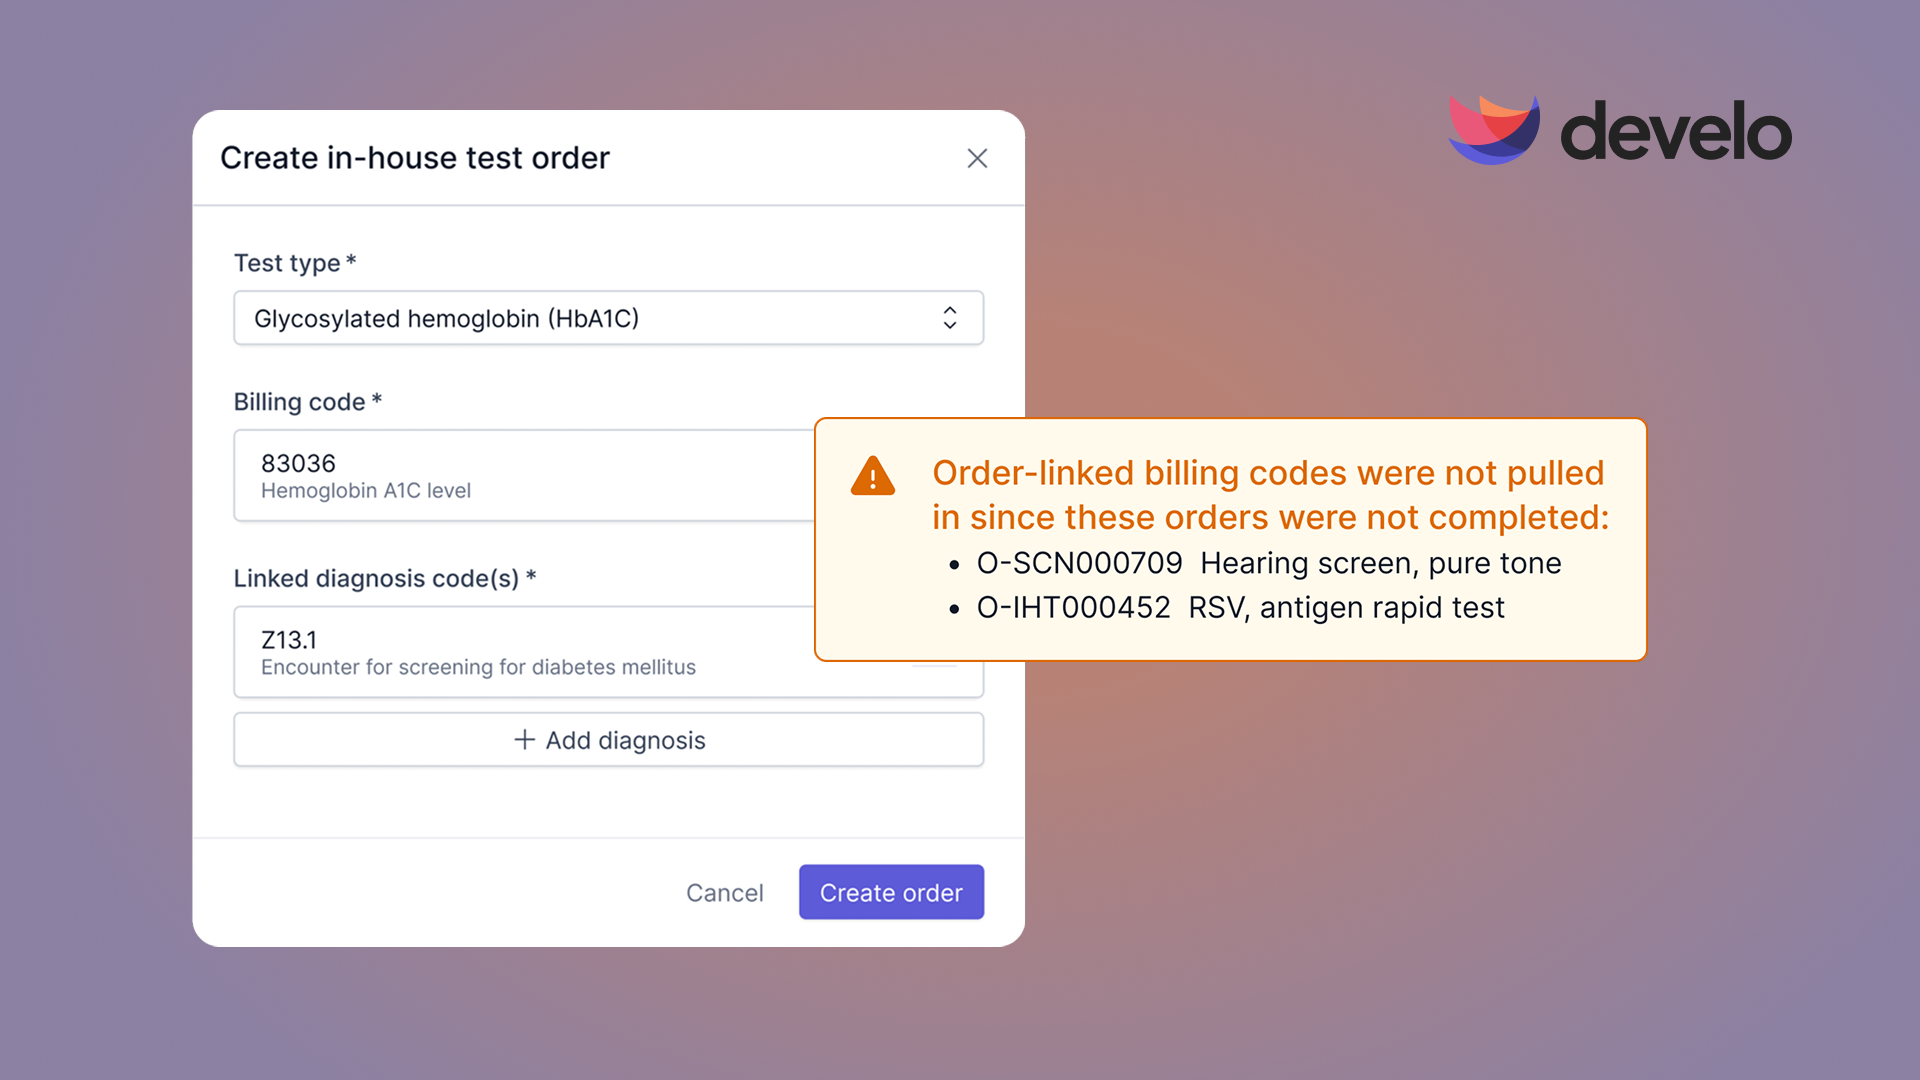
- Automated charge capture: Visit-type rules set codes, units, and modifiers at the point of care, including vaccine administration units for 90460 and 90461 or the 90471–90474 series, calculated from the number of vaccines and components given. You confirm every code before the claim goes out.
- Visit details documented automatically: Every order and its status, the diagnoses for the visit, and the results of each screen and test go into the note as they happen. So do vaccines given and any vaccine, screen, or test a family or patient refused, along with the reason. None of it is carried forward from the last note.
- Documentation in and between visits: Phone calls and updates between visits are documented directly on the chart, with no placeholder visit to create first. Medical assistants, nurses, and pediatricians can work in the same visit at the same time, so intake never holds up the exam note and the exam never holds up intake.
- Pediatric visit templates: Well child templates bring in orders, diagnoses, patient education, and billing codes, not just note text. Develo AI scribe works from the same template and updates its pre-filled findings to match what was discussed in the visit, so the note reflects this visit rather than the template's defaults.
- Adolescent confidentiality: Sensitive details go to a dedicated adolescent confidential section, and Develo saves two versions of the visit note: a complete one for the adolescent and one without the confidential documentation for parents. Family portal access follows each caregiver's guardian relationship.
- Audit-ready records: Every entry and edit is stamped automatically with the user, date, and time. Each user signs in with their own login and multi-factor authentication, remote access can be restricted, and logins, logouts, and EMR activity are logged. A change after signing is saved as an addendum with a new signature date and time, while the original signed note stays intact.
- Digital screenings: Age-appropriate screeners are sent out before the visit and returned scored, so the instrument and score are ready in the chart when you sit down to review them.
- Growth charts: Measurements plot automatically on the right CDC, WHO, or Down syndrome chart, with percentiles, Z-scores, and corrected-age plots, so the note can cite the trend, not just today's number.
Develo can draft the note and set the codes and help free up time spent typing, but the reasoning in the note remains the clinician's responsibility.
Book a demo to see how it works for your types of visits.
Frequently Asked Questions
What Are the Best Practices for EMR Documentation?
The best practices for EMR documentation are charting during the visit, naming the historian, and showing your reasoning. Including clear follow-up instructions and reading through anything copied forward are also crucial.
What Are the Standards for Clinical Documentation?
Clinical documentation standards require that notes identify who wrote them, reflect the patient in front of you, and get completed promptly. Notes also need to be short and clear, so a colleague can find key details quickly.
Is Copy-Paste Allowed in EMR Documentation?
Yes, copy-paste is allowed in EMR documentation within your organization's policy limits. Older, unchanging history is usually safe to copy, but read anything you bring forward before you sign, to keep errors from snowballing.
How Do You Write Good EMR Templates?
You write good EMR templates by giving each visit type its own set of questions and checking every pre-filled finding against the exam. Most systems pre-fill normal findings to save time, and those defaults tend to get accepted without a second look, so correct or remove anything this visit didn't support. Revisit your templates every year as guidance and payer rules shift.
Can an AI Scribe Help With EMR Documentation?
Yes. An AI scribe drafts the note from the visit conversation, which helps with charting in real time and capturing the historian's account in their own words. The clinician still reviews every section and owns the reasoning before signing. In Develo, the AI scribe also reads chart data such as growth, immunizations, and screening results, and works from the visit template so pre-filled findings match what was discussed.